Tue, Oct 13, 2026
Volume 12 - Contnious Publishing
Iran J Neurosurg 2026, 12 - Contnious Publishing: 0-0 |
Back to browse issues page



Download citation:
BibTeX | RIS | EndNote | Medlars | ProCite | Reference Manager | RefWorks
Send citation to:


BibTeX | RIS | EndNote | Medlars | ProCite | Reference Manager | RefWorks
Send citation to:
Barati H, Homaei Rad E, Fattahi E. Structural Resilience at Low Cost: Rethinking Spinal Cord Injury Prevention. Iran J Neurosurg 2026; 12 : 7
URL: http://irjns.org/article-1-562-en.html
URL: http://irjns.org/article-1-562-en.html


1- Guilan Road Trauma Research Center, Trauma Institute, Guilan University of Medical Sciences, Rasht, Iran
2- Social Determinants of Health Research Center, Trauma Institute, Guilan University of Medical Sciences, Rasht, Iran.
3- Department of Health Education and Promotion, School of Health, Guilan University of Medical Sciences, Rasht, Iran ,Esmaeil.fattahi1@gmail.com
2- Social Determinants of Health Research Center, Trauma Institute, Guilan University of Medical Sciences, Rasht, Iran.
3- Department of Health Education and Promotion, School of Health, Guilan University of Medical Sciences, Rasht, Iran ,
Keywords: Spinal cord injury, Road traffic collisions, Injury prevention, Emergency medical services, Health equity, Systems resilience
Full Text [PDF 831 kb]
(190 Downloads)
| Abstract (HTML) (764 Views)
Full Text: (61 Views)
Introduction
Spinal cord injury (SCI) represents one of the gravest adverse outcomes in spine and trauma settings. Despite advances in acute management, the long-term functional, psychological, and socioeconomic impact of SCI remains substantial, and the burden is distributed unevenly across settings [1-3]. Over the past decade, epidemiologic syntheses and global analyses have improved our ability to describe where SCI risk concentrates and how it changes over time [1-5]. For traumatic SCI in particular, road traffic collisions (RTCs) continue to represent a major pathway-especially in settings undergoing rapid motorization and uneven road-safety protections [2, 4].
However, improved prediction does not automatically translate into fewer catastrophic outcomes. For RTC-related SCI, severity and early deterioration are shaped not only by the crash event but also by system characteristics: The road environment, which influences impact forces; variation in vehicles and protective features; the reliability of prehospital and referral pathways; and social and financial conditions that affect timely access to appropriate care. In other words, prediction has matured, but the “fragility” of everyday mobility systems often remains unchanged. As a result, similar collision mechanisms can yield very different outcomes across jurisdictions.
In this commentary, preventive resilience architecture (PRA) is introduced as a newly proposed conceptual framework developed by the authors. PRA is grounded in established scientific concepts, including injury prevention, safe system thinking, the Haddon matrix, resilience engineering, resilient healthcare, and pathway reliability. Its purpose is to integrate these complementary but often separately discussed concepts into a practical, system-oriented framework for SCI prevention after RTCs.
This study proposes a pragmatic framework, PRA, to complement established road-safety approaches by explicitly targeting the chain from hazard to injury severity to early care. PRA is not intended to replace “safe systems” thinking; rather, it offers a spine-care-relevant lens that asks a specific question: How do we reduce the probability that an RTC results in irreversible spinal cord damage, and how do we minimize early deterioration once injury is suspected? The emphasis is on low-cost, measurable interventions that can be implemented through cross-sector action while remaining meaningful to spine clinicians and spine societies. From crash risk to catastrophic outcome: where systems matter most, RTCs are often framed as failures of driver behavior or enforcement. While these elements are important, RTC-related SCI illustrates the limits of an individual-responsibility narrative. At the population level, injury severity is strongly influenced by structural factors, speed management, road design, protection of vulnerable road users, and the availability and reliability of emergency response. In many regions, traffic laws exist, but enforcement is inconsistent; pedestrian infrastructure is limited; vehicles vary in safety features; and emergency response is delayed by distance, cost barriers, or fragmented coordination [6]. Under such conditions, the difference between a survivable collision and a paralyzing collision may be determined by system design and early pathway performance, not only by the hazard itself.
For the spine community, this framing has two implications. First, SCI prevention [7] should include interventions that reduce the severity of impact when collisions occur (not only the collision frequency). Second, downstream expertise in SCI care can inform upstream priorities, particularly where early deterioration may be reduced through more reliable prehospital and referral pathways.
Preventive resilience architecture
PRA organizes prevention into three interacting pillars. The aim is to disrupt the pathway from RTC hazards to catastrophic spinal injury and early deterioration (Figure 1).
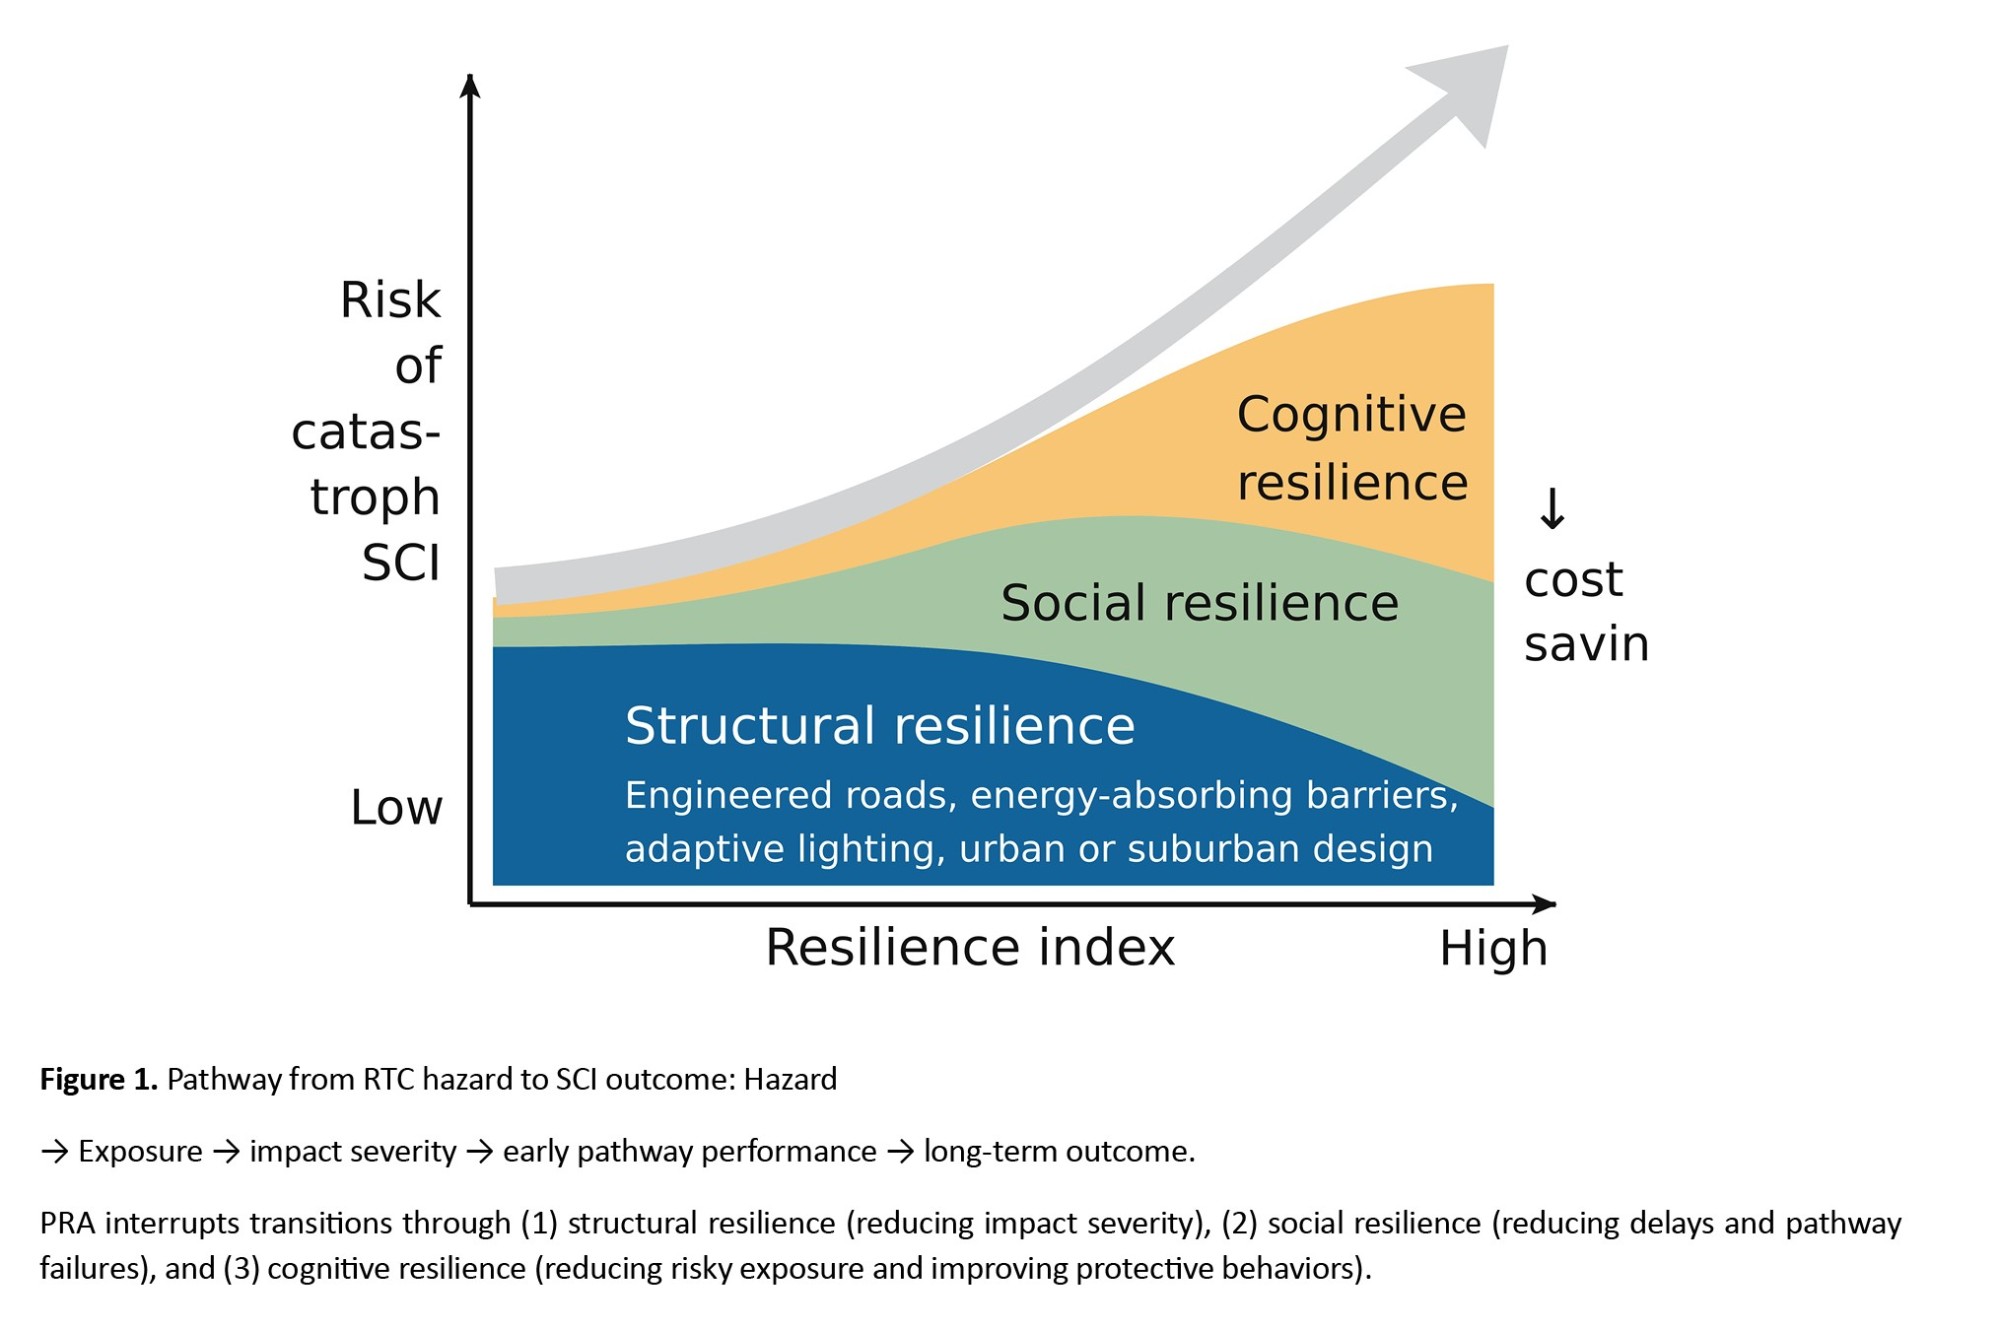
Structural resilience: Design that reduces injury severity
Structural resilience refers to built-environment and mobility-system choices that reduce force transmission and mitigate injury severity. Examples of RTC-related SCI prevention measures include speed-calming road layouts in high-risk corridors, safer intersection designs, forgiving roadside features, improved lighting in collision-prone areas, and infrastructure that protects pedestrians and motorcyclists. Such measures are often feasible without waiting for long-term infrastructure overhauls, especially when targeting high-burden locations identified through routine crash and emergency medical services (EMS) data.
The relevance to spine care is direct: interventions that reduce kinetic energy exchange and blunt peak forces plausibly reduce the incidence of severe spinal injury, even when collisions remain frequent. Prioritization is key, focusing on sites where high-speed impacts and vulnerable road user exposure intersect.
Social resilience: Early pathway reliability and reduced delay
Social resilience focuses on whether a suspected spinal injury triggers timely, coordinated, and appropriate care. Delays in prehospital response and early hospital phases may contribute to worse outcomes, reflecting not only clinical capacity but also transport networks, referral coordination, and affordability [1, 3, 5]. Therefore, PRA emphasizes clear referral pathways; coordinated dispatch and transport; and basic financial protections or coverage mechanisms that reduce hesitation to seek care. Importantly, this pillar is not a call for complex or expensive reforms. Even modest improvements, such as mapping and publicizing referral routes for suspected SCI, strengthening dispatch coordination, and standardizing transfer communication, can reduce variability. From a clinical perspective, the operational question is whether a region has a reliable pathway from scene to definitive evaluation and management, with minimal avoidable delay.
Cognitive resilience: decision environments, not only education
Cognitive resilience addresses how environments and systems shape behavior. Safety education alone can be fragile, and its effects may decay over time and be constrained by structural realities. PRA favors behavioral supports that make safer choices easier: Clear speed cues, visible enforcement aligned with high-risk corridors, targeted campaigns for helmet and seatbelt use anchored in local norms, and simple dashboards that provide feedback to communities and decision-makers. These efforts are most credible when paired with structural supports, enabling people, not merely instructing them, to behave safely.
Why this framing helps: Prioritization without exaggeration
The economic and ethical rationale for prevention is clear: SCI generates long-term health-system demands and major household impacts [1, 3]. Rather than asserting that any single low-cost intervention will transform incidence, PRA advocates a targeted portfolio of low-cost structural and system changes, selected using local data and evaluated with simple indicators. The goal is to reduce catastrophic outcomes and inequities by improving the resilience of everyday mobility systems.
Even modest spending on PRA-aligned actions (e.g. targeted speed management, safer crossings, and streamlined referral/transfer coordination) is small compared with the long-term costs that follow catastrophic SCI and the broader economic losses associated with road traffic injuries. In a population-based Ontario study, the net lifetime direct health-care cost attributable to SCI was estimated at approximately CAD $336,000 per person, with a substantial share incurred in the first year post-injury [8]. In parallel, road traffic injuries generate major societal losses through treatment costs and productivity impacts, costing most countries approximately 3% of gross domestic product [6]. Framed this way, low-cost structural and pathway-strengthening interventions are better understood as investments in population health, with the potential to avert lifelong expenditures and reduce disability burden, rather than discretionary costs.
What the spine community can do now: A 12-nonth starter package
The following actions are feasible within 12 months in many settings and align directly with RTC-related SCI prevention [9-11]:
Structural (where severe collisions concentrate)
Use existing police/EMS records to identify 10–20 high-risk road segments/intersections for severe RTCs and implement targeted speed-calming and lighting improvements where feasible [6].
Prioritize pedestrian and motorcyclist protection at transit stops, markets, and known crossing points (e.g. safe crossings, refuge islands, barriers where appropriate).
Adopt a “high-risk corridor” strategy: concentrate modest resources where severe crashes cluster rather than dispersing small changes widely.
Social (pathway reliability)
Publish a simple, region-specific referral pathway for suspected SCI (whom to call, where to transport, and escalation options).
Improve dispatch and transfer coordination (standardized communication, contact points, and transfer agreements between facilities).
Track avoidable delays using a small set of time points (dispatch, arrival, transfer decision, arrival at receiving facility).
Cognitive (behavioral supports that scale)
Implement targeted messaging on speed and protective equipment focused on the highest-risk user groups and corridors.
Create a basic monthly dashboard for accountability: severe RTCs in target sites, median response/transfer times for suspected SCI, and number of treated sites.
Minimal indicators (interpreted cautiously)
Minimal indicators may include median prehospital response time for suspected severe RTCs; proportion of suspected SCI transported through a defined pathway; number of high-risk sites treated; and severe RTC counts in treated corridors (interpreted alongside exposure) [12].
Conclusion
RTCs remain a major driver of traumatic SCI in many regions. Better prediction can describe where the burden concentrates, but it cannot reduce catastrophic outcomes. Prevention is more likely to advance when mobility systems and early care pathways become less fragile, when roads, vehicles, and response systems are designed to prevent common hazards from producing irreversible spinal injury, and when suspected injury triggers a reliable pathway to timely care. PRA offers a practical way to organize this work for the spine community by linking structural design, pathway reliability, and behavioral supports into measurable, low-cost actions. In this view, prevention becomes a shared responsibility grounded in system design and implementation, not solely in individual risk-taking.
References
Spinal cord injury (SCI) represents one of the gravest adverse outcomes in spine and trauma settings. Despite advances in acute management, the long-term functional, psychological, and socioeconomic impact of SCI remains substantial, and the burden is distributed unevenly across settings [1-3]. Over the past decade, epidemiologic syntheses and global analyses have improved our ability to describe where SCI risk concentrates and how it changes over time [1-5]. For traumatic SCI in particular, road traffic collisions (RTCs) continue to represent a major pathway-especially in settings undergoing rapid motorization and uneven road-safety protections [2, 4].
However, improved prediction does not automatically translate into fewer catastrophic outcomes. For RTC-related SCI, severity and early deterioration are shaped not only by the crash event but also by system characteristics: The road environment, which influences impact forces; variation in vehicles and protective features; the reliability of prehospital and referral pathways; and social and financial conditions that affect timely access to appropriate care. In other words, prediction has matured, but the “fragility” of everyday mobility systems often remains unchanged. As a result, similar collision mechanisms can yield very different outcomes across jurisdictions.
In this commentary, preventive resilience architecture (PRA) is introduced as a newly proposed conceptual framework developed by the authors. PRA is grounded in established scientific concepts, including injury prevention, safe system thinking, the Haddon matrix, resilience engineering, resilient healthcare, and pathway reliability. Its purpose is to integrate these complementary but often separately discussed concepts into a practical, system-oriented framework for SCI prevention after RTCs.
This study proposes a pragmatic framework, PRA, to complement established road-safety approaches by explicitly targeting the chain from hazard to injury severity to early care. PRA is not intended to replace “safe systems” thinking; rather, it offers a spine-care-relevant lens that asks a specific question: How do we reduce the probability that an RTC results in irreversible spinal cord damage, and how do we minimize early deterioration once injury is suspected? The emphasis is on low-cost, measurable interventions that can be implemented through cross-sector action while remaining meaningful to spine clinicians and spine societies. From crash risk to catastrophic outcome: where systems matter most, RTCs are often framed as failures of driver behavior or enforcement. While these elements are important, RTC-related SCI illustrates the limits of an individual-responsibility narrative. At the population level, injury severity is strongly influenced by structural factors, speed management, road design, protection of vulnerable road users, and the availability and reliability of emergency response. In many regions, traffic laws exist, but enforcement is inconsistent; pedestrian infrastructure is limited; vehicles vary in safety features; and emergency response is delayed by distance, cost barriers, or fragmented coordination [6]. Under such conditions, the difference between a survivable collision and a paralyzing collision may be determined by system design and early pathway performance, not only by the hazard itself.
For the spine community, this framing has two implications. First, SCI prevention [7] should include interventions that reduce the severity of impact when collisions occur (not only the collision frequency). Second, downstream expertise in SCI care can inform upstream priorities, particularly where early deterioration may be reduced through more reliable prehospital and referral pathways.
Preventive resilience architecture
PRA organizes prevention into three interacting pillars. The aim is to disrupt the pathway from RTC hazards to catastrophic spinal injury and early deterioration (Figure 1).
Structural resilience: Design that reduces injury severity
Structural resilience refers to built-environment and mobility-system choices that reduce force transmission and mitigate injury severity. Examples of RTC-related SCI prevention measures include speed-calming road layouts in high-risk corridors, safer intersection designs, forgiving roadside features, improved lighting in collision-prone areas, and infrastructure that protects pedestrians and motorcyclists. Such measures are often feasible without waiting for long-term infrastructure overhauls, especially when targeting high-burden locations identified through routine crash and emergency medical services (EMS) data.
The relevance to spine care is direct: interventions that reduce kinetic energy exchange and blunt peak forces plausibly reduce the incidence of severe spinal injury, even when collisions remain frequent. Prioritization is key, focusing on sites where high-speed impacts and vulnerable road user exposure intersect.
Social resilience: Early pathway reliability and reduced delay
Social resilience focuses on whether a suspected spinal injury triggers timely, coordinated, and appropriate care. Delays in prehospital response and early hospital phases may contribute to worse outcomes, reflecting not only clinical capacity but also transport networks, referral coordination, and affordability [1, 3, 5]. Therefore, PRA emphasizes clear referral pathways; coordinated dispatch and transport; and basic financial protections or coverage mechanisms that reduce hesitation to seek care. Importantly, this pillar is not a call for complex or expensive reforms. Even modest improvements, such as mapping and publicizing referral routes for suspected SCI, strengthening dispatch coordination, and standardizing transfer communication, can reduce variability. From a clinical perspective, the operational question is whether a region has a reliable pathway from scene to definitive evaluation and management, with minimal avoidable delay.
Cognitive resilience: decision environments, not only education
Cognitive resilience addresses how environments and systems shape behavior. Safety education alone can be fragile, and its effects may decay over time and be constrained by structural realities. PRA favors behavioral supports that make safer choices easier: Clear speed cues, visible enforcement aligned with high-risk corridors, targeted campaigns for helmet and seatbelt use anchored in local norms, and simple dashboards that provide feedback to communities and decision-makers. These efforts are most credible when paired with structural supports, enabling people, not merely instructing them, to behave safely.
Why this framing helps: Prioritization without exaggeration
The economic and ethical rationale for prevention is clear: SCI generates long-term health-system demands and major household impacts [1, 3]. Rather than asserting that any single low-cost intervention will transform incidence, PRA advocates a targeted portfolio of low-cost structural and system changes, selected using local data and evaluated with simple indicators. The goal is to reduce catastrophic outcomes and inequities by improving the resilience of everyday mobility systems.
Even modest spending on PRA-aligned actions (e.g. targeted speed management, safer crossings, and streamlined referral/transfer coordination) is small compared with the long-term costs that follow catastrophic SCI and the broader economic losses associated with road traffic injuries. In a population-based Ontario study, the net lifetime direct health-care cost attributable to SCI was estimated at approximately CAD $336,000 per person, with a substantial share incurred in the first year post-injury [8]. In parallel, road traffic injuries generate major societal losses through treatment costs and productivity impacts, costing most countries approximately 3% of gross domestic product [6]. Framed this way, low-cost structural and pathway-strengthening interventions are better understood as investments in population health, with the potential to avert lifelong expenditures and reduce disability burden, rather than discretionary costs.
What the spine community can do now: A 12-nonth starter package
The following actions are feasible within 12 months in many settings and align directly with RTC-related SCI prevention [9-11]:
Structural (where severe collisions concentrate)
Use existing police/EMS records to identify 10–20 high-risk road segments/intersections for severe RTCs and implement targeted speed-calming and lighting improvements where feasible [6].
Prioritize pedestrian and motorcyclist protection at transit stops, markets, and known crossing points (e.g. safe crossings, refuge islands, barriers where appropriate).
Adopt a “high-risk corridor” strategy: concentrate modest resources where severe crashes cluster rather than dispersing small changes widely.
Social (pathway reliability)
Publish a simple, region-specific referral pathway for suspected SCI (whom to call, where to transport, and escalation options).
Improve dispatch and transfer coordination (standardized communication, contact points, and transfer agreements between facilities).
Track avoidable delays using a small set of time points (dispatch, arrival, transfer decision, arrival at receiving facility).
Cognitive (behavioral supports that scale)
Implement targeted messaging on speed and protective equipment focused on the highest-risk user groups and corridors.
Create a basic monthly dashboard for accountability: severe RTCs in target sites, median response/transfer times for suspected SCI, and number of treated sites.
Minimal indicators (interpreted cautiously)
Minimal indicators may include median prehospital response time for suspected severe RTCs; proportion of suspected SCI transported through a defined pathway; number of high-risk sites treated; and severe RTC counts in treated corridors (interpreted alongside exposure) [12].
Conclusion
RTCs remain a major driver of traumatic SCI in many regions. Better prediction can describe where the burden concentrates, but it cannot reduce catastrophic outcomes. Prevention is more likely to advance when mobility systems and early care pathways become less fragile, when roads, vehicles, and response systems are designed to prevent common hazards from producing irreversible spinal injury, and when suspected injury triggers a reliable pathway to timely care. PRA offers a practical way to organize this work for the spine community by linking structural design, pathway reliability, and behavioral supports into measurable, low-cost actions. In this view, prevention becomes a shared responsibility grounded in system design and implementation, not solely in individual risk-taking.
References
- GBD Spinal Cord Injuries Collaborators. Global, regional, and national burden of spinal cord injury, 1990–2019: A systematic analysis for the global burden of disease study 2019. The Lancet Neurology. 2023; 22(11):1026-47. [DOI:10.1016/S1474-4422(23)00287-9] [PMID] [PMCID]
- Lu Y, Shang Z, Zhang W, Pang M, Hu X, Dai Y, et al. Global incidence and characteristics of spinal cord injury since 2000-2021: A systematic review and meta-analysis. BMC Medicine. 2024; 22(1):285. [DOI:10.1186/s12916-024-03514-9] [PMID] [PMCID]
- Furlan JC, Sakakibara BM, Miller WC, Krassioukov AV. Global incidence and prevalence of traumatic spinal cord injury. Canadian Journal of Neurological Sciences, 2013. 40(4):456-64. [DOI:10.1017/S0317167100014530] [PMID]
- Jazayeri SB, Beygi S, Shokraneh F, Hagen EM, Rahimi-Movaghar V. Incidence of traumatic spinal cord injury worldwide: a systematic review. European Spine Journal. 2015; 24(5):905-18. [PMID] [DOI: 10.1007/s00586-014-3424-6]
- Rahimi-Movaghar V, Sayyah MK, Akbari H, Khorramirouz R, Rasouli MR, Moradi-Lakeh M, et al. Epidemiology of traumatic spinal cord injury in developing countries: A systematic review. Neuroepidemiology. 2013; 41(2):65-85. [DOI:10.1159/000350710] [PMID]
- WHO. Global status Report on road safety 2023: Country and territory profiles. Geneva: World Health Organization; 2024. [Link]
- Akbari M, Heydari ST, Razzaghi A, Vali M, Tabrizi R, Bagheri Lankarani K. Effectiveness of interventions for preventing road traffic injuries: A systematic review in low-, middle- and high-income countries. PLoS One. 2024; 19(12):e0312428.[DOI:10.1371/journal.pone.0312428] [PMID] [PMCID]
- Chan BC, Cadarette SM, Wodchis WP, Krahn MD, Mittmann N. The lifetime cost of spinal cord injury in Ontario, Canada: A population-based study from the perspective of the public health care payer. The Journal of Spinal Cord Medicine. 2019. 42(2):184-93. [DOI:10.1080/10790268.2018.1486622] [PMID] [PMCID]
- M Selveindran S, Tango T, Khan MM, Simadibrata DM, Hutchinson PJA, Brayne C, et al. Mapping global evidence on strategies and interventions in neurotrauma and road traffic collisions prevention: A scoping review. Systematic Review. 2020; 9(1):114. [DOI:10.1186/s13643-020-01348-z] [PMID] [PMCID]
- Banstola A, Mytton J. Cost-effectiveness of interventions to prevent road traffic injuries in low- and middle-income countries: A literature review. Traffic Injury Prevention. 2017; 18(4):357-62. [DOI:10.1080/15389588.2016.1212165] [PMID]
- Delaney PG, Eisner ZJ, Pine H, Klapow M, Thullah AH, Bamuleke R, et al. Leveraging transportation providers to deploy lay first responder (LFR) programs in three sub-Saharan African countries without formal emergency medical services: Evaluating longitudinal impact and cost-effectiveness. Injury. 2024; 55(5):111505. [DOI:10.1016/j.injury.2024.111505] [PMID]
- Ahn H, Singh J, Nathens A, MacDonald RD, Travers A, Tallon J, et al. Pre-hospital care management of a potential spinal cord injured patient: a systematic review of the literature and evidence-based guidelines. Journal of Neurotrauma. 2011; 28(8):1341-61. [DOI:10.1089/neu.2009.1168] [PMID] [PMCID]
Type of Study: Letter to Editor |
Subject:
Neurotrauma
Send email to the article author
| Rights and Permissions | |
 |
This work is licensed under a Creative Commons Attribution-NonCommercial 4.0 International License. |

Copyright © The Author(s);
This is an open access article distributed under the terms of the Creative Commons Attribution License (CC-By-NC), which permits use, distribution, and reproduction in any medium, provided the original work is properly cited and is not used for commercial purposes.
Contact Information
This is an open access article distributed under the terms of the Creative Commons Attribution License (CC-By-NC), which permits use, distribution, and reproduction in any medium, provided the original work is properly cited and is not used for commercial purposes.
Contact Information
